Rogue AI, Malicious Bots and the End of Humanity

Recently I received an unusual email which stated that ‘AI read your paper The Lancaster Hospital Coade Stone’, a rather obscure publication of mine from 2014, published originally in the now defunct Morecambe Bay Medical Journal, writes Bryan Rhodes.

Black and white photo from an old BBC sitcom with a female soothsayer

Forebodings from Senna the soothsayer in the classic British TV comedy Up Pompeii! © BBC Archives

Should I be worried that AI has started to digest all medical history publications in an effort to find secret ways to exterminate the human race? Or should I be delighted that a superintelligent computer system has finally recognised the value of my research into this very durable ceramic artwork, produced in Eleanor Coade’s manufactory more than 200 years ago?

Having read that an AI system had recently deciphered a coded German submarine message from WW1 in just a few hours when human decoders had failed to achieve this for over a century, my initial reaction was that perhaps the AI had failed to appreciate the difference between Hospital Coade and Hospital Code.

After all, the Australian Government has been alarmed by the way an AI test resulted in ‘swarms of rogue AI agents’ hacking their way into one of their healthcare systems, an event that they were only made aware of some months later. Most British hospitals now rely very heavily on digital systems and paperless healthcare records. The British Library suffered a major cyberattack in 2023 and has only partially recovered, access to precious past editions of the BSHM’s publication Topics in the History of Medicine, for example, has not yet been fully restored.

The risks to archives are threefold: hacking of digital sources such as the British Library, replacing real primary sources with less accurate digital copies, also known as AI slop and the transfer of resources from local government archives into AI generated activity.

In this National Year of Reading, it was shocking to discover that the company Anthropic was feeding books to its version of AI and then pulping the digested books. The Bodleian Library has announced that they will be allowing Open AI to access their antiquarian books, and one must hope that none of their precious books will meet the same fate as the ones used by Anthropic.

Another intriguing message I have received, while trying to access a historical article on the website for the Royal College of Surgeons Bulletin, stated: ‘This website uses a security system to protect against malicious bots. This message is displayed while the website verifies that you are not a bot.” All I had to do was check a box to confirm my human status. Could malicious bots disrupt our access to historical archives and journals?

Forebodings

Far worse, is it possible that swarms of rogue AI agents teaming up with some of these malicious bots could somehow threaten the future of the human race? How can this be prevented?

Evan Hubinger, a former manager at Anthropic AI, has suggested that there is a greater than 10% chance that AI could cause human extinction within the next decade, an assessment with which the Nobel laureate and computer science expert, Geoffrey Hilton, has concurred. Although such forebodings always seem to evoke memories of Senna the soothsayer, the pessimistic character featured in the classic British TV comedy Up Pompeii!, perhaps we should be more concerned about these new AI warnings. The Lancet certainly seems to be so.

In 2022, the Lancet established the Commission on 21st Century Global Threats to Health, and their first report was published in October 2026. The commission, featuring many of the world’s leading authorities on global health, looked at 17 major threats within the current century. Two of these threats, nuclear conflict and malicious use of AI, were considered to sufficiently dangerous to pose an extinction threat to humanity, though the scale of the risk was difficult to quantify.

The Lancet Commission considered that there were three main mechanisms whereby malicious use of AI could pose a significant threat. First, with the development of novel forms of bioweapons, second, by the infiltration of malicious AI into crucial infrastructure such as healthcare systems, and finally the loss of control to AI systems that have sub-goals which can harm human populations.

During a visit to a local university campus. I spotted a display of books and booklets with Isaac Asimov’s novel I, Robot placed in front of a book about AI. When I was a teenager, Asimov was one of my favourite authors, and he wrote a series of books and short stories featuring humanoid robots, possibly inspired by the recent invention of robots like the giant Elektro, created in the 1930s.

In a 1942 short story, Runaround, Asimov introduced the ‘Three Laws of Robotics’, which included an over-riding first law stating: ‘A robot cannot harm a human or allow one to come to harm through inaction’. Asimov felt that these three laws, which were installed into every robot’s central programming, left enough ambiguity for him to create interesting storylines for his novels.

Could such pre-programmed ethical frameworks be installed as safeguards in AI super-computer systems ? Can humanity control its own inventions? Or will AI move beyond slop and digital disruption to become the 21st century version of Frankenstein’s monster?

Bryan Rhodes is a retired orthopaedic surgeon and Vice President of BSHM.

Further reading: Murray, C.J.L. et. al. The Lancet Commission on 21st Century Global Threats to Health, The Lancet, 17 Oct. 2026, Vol. 408, pp 1603-61


Dora Colebrook: pioneer of the randomised controlled trial?

Dora Challis Colebrook (1884 – 1965) has, in my opinion, been overlooked as the architect of the first randomised controlled trial (RCT) in Britain, says Martin Edwards.

The trial in question concerned light therapy. The 1920s saw a ‘boom’ in enthusiasm for treating all manner of medical conditions with bright light, particularly ultraviolet (UV). Hospitals all around Britain opened light therapy departments, private doctors offered the treatment and manufacturers sold units for the public to use at home. Britain’s dull, smog-congested cities were thought to render its inhabitants particularly suitable for light therapy, which rapidly became regarded as a panacea.

Promoting  light therapy

The Medical Research Council (MRC), created in 1911 as the Medical Research Committee, was at this time attempting to position itself as the only organisation properly able to test therapeutic efficacy. The explosion of light therapy caught the MRC on the hop. Eager to evaluate the treatment before its popularity made its opinion irrelevant, the MRC sought a worker in the field. Thanks to an influential MRC member, the bacteriologist Leonard Colebrook (1883 – 1967), they lighted upon Dora Colebrook – Leonard’s sister.

Dora was a doctor, trained at the Royal Free Hospital in London. After a stint as a gynaecologist in Sheffield and some years in Cambridge as a GP, she worked in an infant welfare centre in Islington administering light therapy to physically feeble children. Asked in 1925 by Walter Morley Fletcher, the MRC Chair, to summarise her experience she described an ‘almost monotonous’ increase in liveliness, vigour, weight gain and general wellbeing among the children she treated. Fletcher asked her to submit a research proposal. Inexperienced in research, Colebrook initially offered a hopelessly ambitious scheme which Fletcher rejected. There followed one or more conversations with someone unspecified from the MRC, and Colebrook submitted a revised proposal for a study which she performed in 1927.

The trial

Colebrook randomly divided 300 children ‘by drawing lots’ into three groups. One received UV therapy, the second ‘sham’ therapy from a lamp screened by UV-excluding glass, and the third was untreated. Colebrook recorded the children’s heights, weights, incidence of infections, school absences and subjective impressions from teachers, parents and herself. Her results were unequivocally negative, demonstrating no apparent benefit of light treatment, and were published in an MRC special report in 1929.[1]

The response was immediate and vitriolic. Doctors, unqualified light therapy practitioners, manufacturers and the public joined in the vilification of Dora, referring to her in medical journals and lay newspapers in isolation, implying that she was a lone maverick researcher, without reference to the MRC. Her gender was repeatedly stressed, the Daily Telegraph describing her simply as ‘a woman writer.’ Dora faced equal vitriol in person at medical meetings where her findings were dismissed with frank disbelief, doctors preferring the subjective opinion of more distinguished medical figures. Eventually the furore fizzled out; Dora went on to work with her brother Leonard on antibacterial therapy, and her light study, something of an embarrassment to the MRC due to its reception, was quietly forgotten.

This was a clash of epistemologies; a new ‘scientific’ therapeutic assessment versus the traditional wisdom and experience of experts. But Dora was sidelined, not simply because she was presenting an unexpected and unpopular finding, but because her relatively lowly status in the medical hierarchy, and her gender, enabled opponents to single her out for opprobrium.

Her study is arguably the first true RCT in this country. Yet when the MRC chose an exemplar to promote the RCT as its own invention, it employed the streptomycin trial of 1948 – a popular trial of a supposed ‘wonder drug’ which provided the positive results that everybody wanted and expected.  Had Dora’s critics been more amenable to evidence, and the MRC less embarrassed by her reception, hers might have been recognised as the first true RCT.

Martin Edwards worked for more than 30 years as a GP in South London while pursuing an interest in history of medicine, gaining an MSc in history of science and medicine at Imperial College in 1998 and an MD in history of medicine from UCL in 2004. His interests include the evaluation of therapeutic efficacy and therapeutic bedrest in the 19th century.

[1]      D. Colebrook, Irradiation and Health (London: HMSO, 1929).

Extracts of the report: https://www.jameslindlibrary.org/colebrook-d-1929/

The Sacra Infermeria or Holy Infirmary of Malta

Founded in 1299, Malta’s Santo Spirito Hospital was more than 200 years old when the Knights Hospitalier arrived on the island and decided a new hospital was needed. Arpan Banerjee tells the story of a hospital ahead of its time.

The Knights Hospitalier were a proud military order of the Catholic Church founded in the 11th century to fight as a military force  in the Crusades and also take care of the sick. After the fall of Jerusalem, they eventually migrated to Malta in 1530 where they stayed and ruled the islands until 1798 when they were defeated by Napoleon Bonaparte.

Sacra Infermeria today: author’s photo

At the time of their arrival, Santo Spirito Hospital was the country’s main hospital, but it was outside Rabat, some distance from Valletta. The Knights Hospitaliers felt a hospital was required in Valletta, now the capital of Malta, and in 1574 they built the Sacra Infermeria or Holy Infirmary, at the northern tip of the small promontory of land surrounded by the Grand Harbour. It became one of the leading hospitals in Europe.

A modern hospital

The Sacra Infermeria Hospital had around 500 beds, but could expand to accommodate almost 900 patients if needed. Although not called such then, the Nightingale-style wards included one of the largest halls of its time. The Old Ward, as it was known, was more than 150 metres long. A small ward served the dying. In the basement was a 100-bedded ward for wounded or sick soldiers and sailors. The hospital treated not only the sick but also provided accommodation to those on pilgrimage to the Holy Land. What made the hospital unique, however, were the facilities, the most modern of the time, and high standards of care long before Florence Nightingale made known the importance of nursing.

In the seventeenth century, the hospital boasted a school of anatomy and surgery founded by the Grand Master Cotoner. Cadaveric dissection took place, which did not become a routine part of medical training until the eighteenth century and beyond in Britain. In addition, Sacra Infermeria had a wing for patients with infectious diseases and a ward for the mentally ill patients.

After the brief rule of Malta by the French, the British took over in 1800, and the hospital became an important base for wounded soldiers, as well as the local sick. It played an important role in the Crimean War and First World War due to its strategic position in the Mediterranean, south of Sicily, and known as the Station Hospital.

The Great Ward of the Station Hospital, Malta c 1906, public domain

The hospital was decommissioned in 1918 after WW1 ended. In WW2, the hospital building survived partial bombing, and after the war it served briefly  as a base for the Allied troops based in Malta. The Maltese police then took over the site. A new general hospital was commissioned in Malta in the 1920s, St Luke’s Hospital outside Valletta, and this was replaced by the current teaching hospital Mater Dei in 2007.

Today the old building of the Sacra Infermeria has been renovated internally and converted into a conference centre. The Great Hall  survives and is a reminder of the hospital’s illustrious past and important place in medical history. The Knights of St John no longer rule Malta but exist as the Sovereign Military Order of Malta (SMOM) and perform a global humanitarian role and charitable work . The St John Ambulance that operates in Malta is a direct legacy of this order.

Dr Arpan Banerjee is a retired consultant radiologist from Birmingham. He is currently the Chairman of the International Society for the History of Radiology and a past Chairman of the British Society for the History of Radiology. His latest book project was co-editing and contributing to the Pioneers in Radiology Worldwide at the time of Wilhelm Conrad Röntgen.

References

https://en.wikipedia.org/wiki/Mediterranean_Conference_Centre

Mediterranean Conference Centre

https://whc.unesco.org/en/list/131/  City of Valletta

Major-General Sir David Bruce, K.C.B., F.R.S. Nature 129, 84–86 (1932). https://doi.org/10.1038/129084a0


The Hidden Nurse Dictionary

The Lancaster Health and Medical Museum Collection, an affiliated society of BSHM, publishes a short article each month about one of the treasured objects in their collection. Bryan Rhodes describes how one of these objects revealed a hidden book by a remarkable author.

This week marks International Nurses’ Day, and this blog celebrates an interesting nurse dictionary donated to our collection some years ago by an elderly nurse who had trained in Lancaster. Having chosen to feature this book, A New Dictionary for Nurses by Lois Oakes, as our ‘Object of the Month’ for March 2026 on the Lancaster Health and Medical Museum website, I discovered a completely different nurse dictionary hidden inside its damaged cover.

The hidden book’s remarkable author was Violet Honnor Morten (1861 – 1913), who preferred to be known as Honnor Morten. Honnor Morten was not just a nurse and a writer, but also a social activist who lectured widely on family health, women’s rights and nursing care.

A New Dictionary for Nurses by Lois Oakes is small (12 x 9 cm /4.5 x 3.5 inches) and was clearly designed to fit into a pocket. Its well-thumbed and taped cover indicates how much the book was used over the years. The front cover shows that it was first published in 1932. This book, which subsequently became the ‘Churchill Livingstone’s Dictionary of Nursing’, was last published in 2006, the 19th edition.

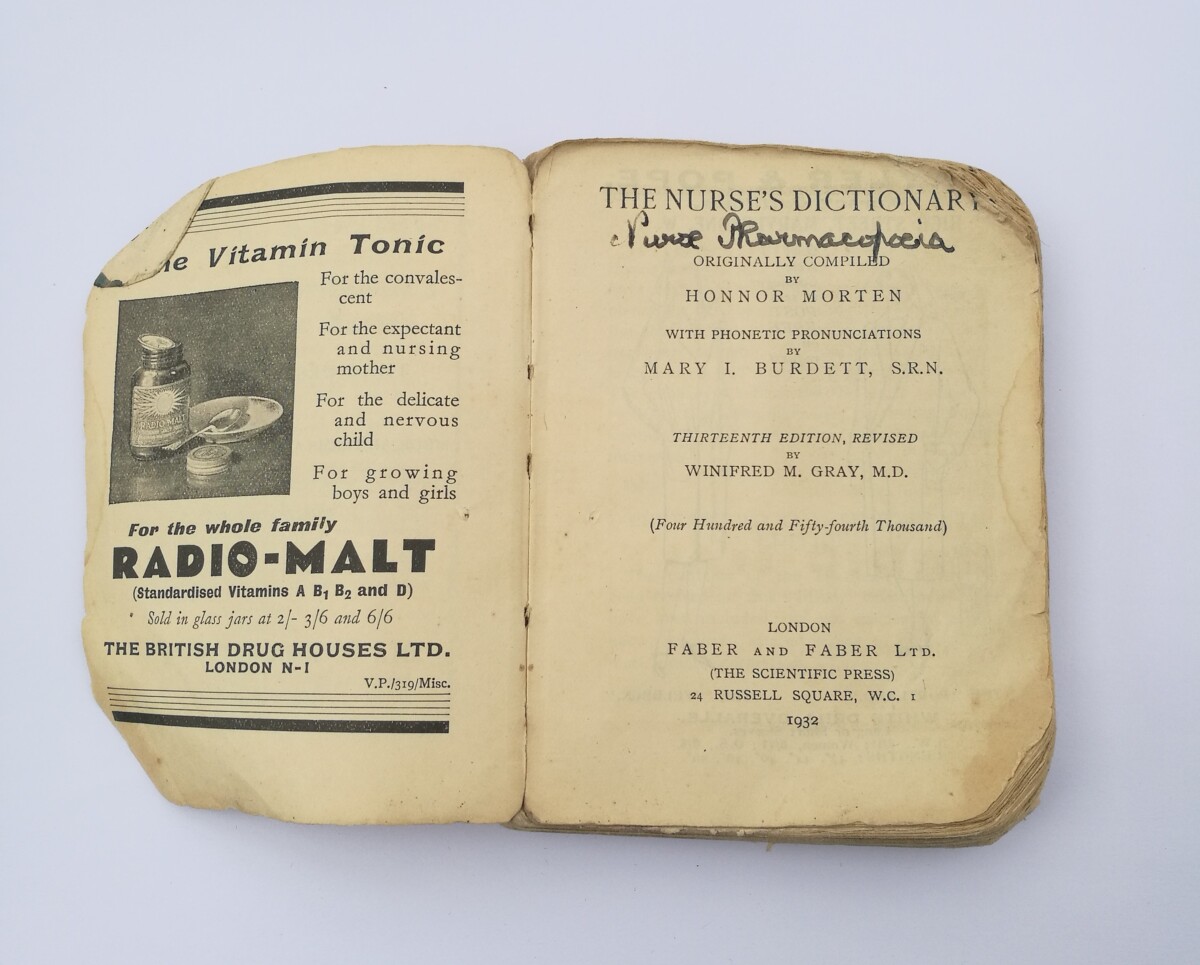
However, the bulk of the contents, easily separated from the cover, is from another pocket-sized nurse dictionary: The Nurse’s Dictionary by Honner Morten, 13th edition, also published in 1932 by Faber and Faber. In 246 pages, featuring entries from abdomen to zymotic, appears to be a complete Honnor Morten dictionary,

The small photograph found inside the book has the inscription ‘Alder Hey 1932-35’ on the reverse, and the date 1932 is also hand-written inside the red cover.

Honner Morten’s dictionary is almost certainly the most successful nursing publication of all time, achieving 30 editions until the 1980s by Faber and Faber, with three further editions published by Mosby. The final 33rd, edition, entitled Mosby Nurse’s Pocket Dictionary, came out in 2005.

Who was Honnor Morten?

(Violet) Honnor Morten (1861-1913), nurse, author and activist, was born in Surrey and was the daughter of a wealthy solicitor and the niece of a successful author called William Black. She started her nurse training in 1881 at the London Hospital and then studied midwifery before gaining a diploma in scientific hygiene at Bedford College, London. A prolific writer, she contributed articles to The Hospital journal, and the same publisher, Scientific Press, published the first edition of her dictionary in 1891. Then titled Nurse’s Dictionary of Medical Terms and Nursing Treatment, it was the first such dictionary dedicated to nurses. The book went through eight editions in her lifetime and was very successful. This book became The Nurse’s Dictionary, ultimately achieving 33 editions. She also wrote a number of other books between 1888 and 1912, mostly on subjects related to nursing, midwifery or childcare.

Early 20th century white woman with short hair, dark dress elaborate white lace collar

digital.library.lse.ac.uk/

An avowed socialist and non-militant suffragist, Morten lectured widely on family health, women’s rights and nursing care. During the campaign for women’s voting rights, she joined others in refusing to pay taxes, resulting in the confiscation and auctioning of some of her property. She was a founder member of a number of societies including the Women’s Writers Club, the Association of Asylum Workers, the Nurse’s Co-operation and the School Nurses’ Society. The latter was involved in efforts to provide countryside respite care for disabled children, and Morten supported this aim by establishing a centre in Rotherfield, Sussex in 1905 for disabled children from London.

A keen smoker at a time when the health risks of smoking were not understood, she died of throat cancer the year before the first world war began, aged just 52. Her most abiding legacy is the pioneering nurse dictionary which continued to inform nurse trainees more than a century after its first publication.


Bryan Rhodes is the chair of the Lancaster Health and Medical Museum Collection. He is a retired orthopaedic surgeon. He is vice-president of the British Society for the History of Medicine and was guest editor of the 5th edition of the BSHM journal Topics in the History of Medicine.

Further reading:

Ross, E. (2022, May 12). Morten, (Violet) Honnor (1861–1913), nurse and journalist. Oxford Dictionary of National Biography. Retrieved 15 Apr. 2026


Oasis of Glass, Desert of Brick: The Peckham Experiment’s Radical Vision

In the interwar years in Britain, a crisis of national fitness exposed by the First World War prompted the Fabian Society to propose a centralised, expert-led welfare state to manage the population from the top down. The Peckham Experiment in south-east London offered a defiant alternative, says Jennifer Okerenta.   

(Wikimedia Commons)

The Peckham Experiment was born a rejection of established medical practice by George Scott Williamson and Innes Pearse, two pathologists working at the Royal Free Hospital. Moving away from a narrow focus on the mechanics of disease, they investigated how health manifests when an organism exists in harmony with its environment. For them, health was not a state-dispensed service; it was a spontaneous by-product of a self-organising community. They choose Peckham as a stable, working class district without extremes of poverty for a community-led experiment.

While the Fabians argued public health should be provided by an elite class of state planners and doctors, Williamson and Pearse championed the social principle. They believed that by removing the paternalism of state-managed welfare, they could observe families thriving autonomously. This commitment to self-governance drew them into radical circles, with Williamson frequently speaking for the London Anarchist Group.

Ethology and the “Sight of Action”

The founders’ unorthodoxy was holistic, extending from the family unit to the soil. At a time when medical progress was measured by clinical cures and agriculture pivoted toward industrial chemicals, Williamson and Pearse became key figures in creating the Soil Association, a charity focussed on the effect of agriculture on the environment. Convinced health was impossible without quality nutrition, they established an organic farm at Bromley Common, Kent. This deliberately bypassed the industrial food system to prove human health remained dependent on land fertility.

(Wikipedia Peckham Experiment)

The ethological approach—observing behaviour in its natural setting—found physical form in the Pioneer Health Centre in Peckham, a building that Bauhaus director Walter Gropius famously dubbed an “oasis of glass in a desert of brick” in 1935.

Designed by Sir Owen Williams, this open architecture facilitated the “sight of action.” This was the hypothesis that health could be caught by observing others. The glass panels allowed biologists to observe the community without the white coat interference that defined traditional hospitals.

Charging a family subscription fee ensured the Pioneer Health Centre in Peckham remained a member-owned club, where health was nurtured through collective participation rather than top-down charity.

Collision with chemical triumphalism

This insistence on localism caused the experiment to collide with the new National Health Service (NHS) in 1948. Uncompromising critics, Williamson and Pearse famously branded it a “national sickness service.” They argued that the state’s focus on acute cures and chemical triumphalism (relying on new drugs like antibiotics) ignored the environmental roots of health.

The Ministry of Health dismissed the autonomous, fee-paying Centre as an ‘administrative irregularity.’ To a new top-down NHS built on hospital beds and pharmacy counters, a community club centred on a swimming pool simply did not compute as healthcare.

When the Centre closed in 1950, Britain abandoned a radical alternative for public health. Today, as we grapple with the limits of a purely curative system, the experiment’s core finding that health is a mutual synthesis of environment and organism feels strikingly modern. It serves as a reminder that health cannot be dispensed from a pharmacy; it must be nurtured within a community, from the ground up.

Jennifer Okerenta is a fourth-year medical student at the University of Manchester. She is a winner of a 2026 Norah Schuster Prize for her paper on which this blog is based. Her research explores the history of social biology, radical politics and the architecture of preventive medicine.

References and further reading

Armstrong, D., Political Anatomy of the Body: Medical Knowledge in Britain in the Twentieth Century. Cambridge: Cambridge University Press, 1983

Conford, P., ‘Smashed by the National Health’? A Closer Look at the Demise of the Pioneer Health Centre, Peckham. Medical History, 2016, Vol. 60, nr. 2, pp. 250-269

Conford, P., Anarchism and the welfare state: the Peckham Health Centre. History & Policy, 2024

Pearse, I. H. & Crocker, L. H., The Peckham Experiment: A study of the living structure of society. London: Allen & Unwin, 1943. Wellcome Collection.

Williamson, G. S. & Pearse, I. H., Science, Synthesis and Sanity. London: Collins, 1965. Wellcome Collection